
Healthcare Real Estate Capital, Matched to Your Deal
Healthcare Real Estate Fund is a healthcare real estate capital provider. We match owners, operators and buyers of urgent care, surgery center, medical office and outpatient properties with banks, credit unions, life companies, CMBS lenders, debt funds and bridge lenders, then put competing term sheets side by side.
Healthcare tenants sign long leases, invest heavily in their space and rarely move. Lenders know it, and the right ones compete for these loans. Our job is to put your deal in front of them.
Thousands of Capital Sources, One Conversation
Institutions have always had capital markets desks shopping their debt across dozens of lenders. Most healthcare property owners call one bank and take the quote. We level that field. Our capital database spans thousands of sources: community and regional banks, credit unions, life insurance companies, CMBS conduits, debt funds and bridge lenders. Each has a different appetite for leverage, term, recourse and asset type. We match your property and goals to the lenders whose programs fit, then bring back multiple term sheets you can compare line by line.
Maturing Debt, Acquisitions and Construction
Loan coming due? Start planning 12 to 18 months out, and go to market no later than six months before maturity. We shop refinancing across lender types so you can compare rate, proceeds, term and prepayment flexibility instead of accepting your bank's extension by default. Buying a building or a second location? We line up acquisition financing early, so your offer carries real certainty of close. Building new or repositioning space? We match construction and value-add projects with lenders who understand pre-leasing, tenant improvements and the build-out costs of clinical space.
For Physicians and Practice Owners Who Own Their Building
For many practices, the building is the largest asset on the balance sheet, and its equity often sits idle. You spend your days with patients, not lenders, so we do the shopping. Scaling to new locations? We can line up build-to-suit financing and partners. Need capital now? Refinance to fund equipment or a partner buyout, or sell the building and lease it back while you stay in place. Either way, we bring options from lenders and buyers who understand medical real estate, and handle the legwork through closing.
Strong Demand Driven By Demographics
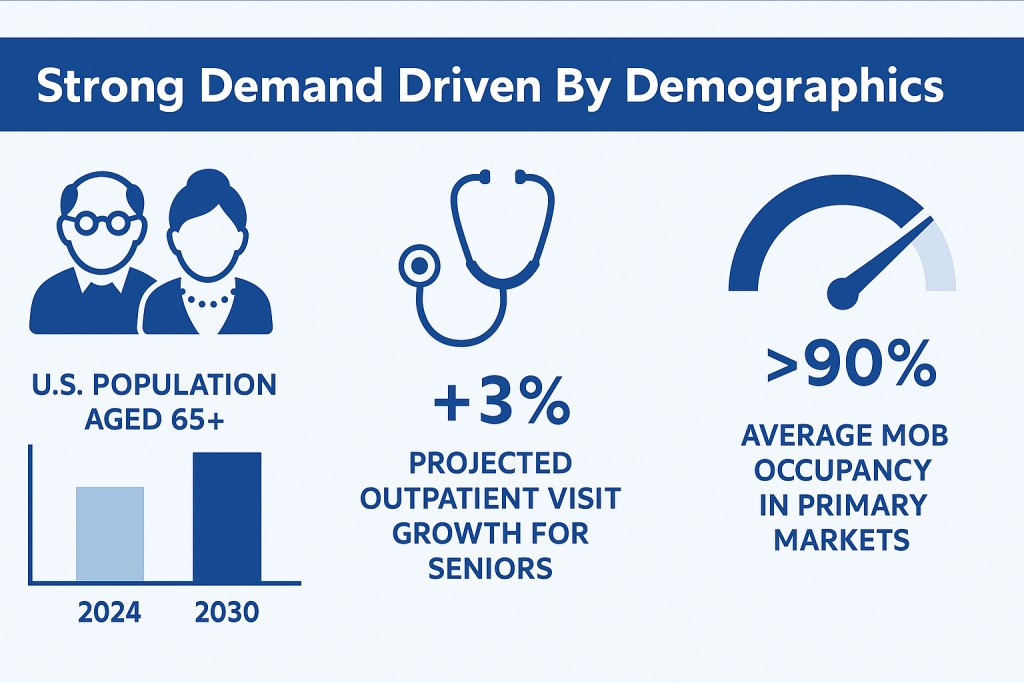
The fastest-growing age groups in America use the most healthcare. That demand runs through physical clinics, surgery centers and medical offices, and it can’t be delayed or moved online.
By 2030, every baby boomer will be 65 or older, and older adults visit doctors and outpatient clinics far more often than working-age adults. That steady rise in visits, procedures and chronic care requires exam rooms, imaging suites and procedure space close to where patients live.
You don’t have to be a physician to own the real estate that serves this demand. Investors buy single-tenant urgent care, dental and medical office buildings outright, alongside the doctors and health systems who lease them on long-term NNN terms.
Own the buildings an aging America depends on, in fee simple, with no fund in between.
Recession Resilient & Defensive Sector
Healthcare is considered a fundamental need, making its demand less sensitive to economic cycles compared to many other real estate sectors. This provides stability for investors, particularly during economic downturns.
Office vacancies spike after layoffs and retail softens when consumers pull back, but patient visits for chronic conditions, screenings and follow-up care continue, funded largely by Medicare, Medicaid and employer insurance. Medical office rent collections held up through the 2008 financial crisis and the pandemic far better than most commercial sectors.

Lenders track that record closely. Healthcare properties are among the assets many banks, life companies and debt funds actively want, so owners refinancing a maturing loan can often negotiate from strength, if they shop the deal widely instead of taking a single quote.
Your property’s resilience is leverage. We put it in front of the lenders who reward it.
Benefiting from the Shift to Outpatient Care
Care is moving out of hospitals and into convenient outpatient settings, and the practices leading that shift need real estate strategies that keep pace.
Procedures that once required a hospital stay now happen in surgery centers, imaging centers and specialty clinics closer to home, and payers encourage it because outpatient care costs less. Practices opening new locations need space built for clinical use. With build-to-suit, a developer and capital partner deliver the building to your specifications, and you lease it long term.
Already own your building? A sale-leaseback converts that equity into growth capital while you stay in place on a long-term lease.
Scale your practice without tying your capital to brick and mortar. We match you with build-to-suit and sale-leaseback partners.
Own 100% of the Building. Keep 100% of the Depreciation.
Single-tenant healthcare NNN properties pair long leases and built-in rent growth with depreciation benefits that belong entirely to you.
Healthcare tenants typically sign initial leases of 7 to 15 years with annual rent increases, and NNN terms generally pass taxes, insurance and most maintenance to the tenant. Across the healthcare NNN properties we track for sale nationwide, asking cap rates run from about 5 to 9 percent, with most between 5.5 and 7 percent, depending on tenant credit, lease term and location.
Because you own the property outright, every dollar of depreciation is yours. A cost segregation study can reclassify part of the building into shorter-lived components, and with 100% bonus depreciation now permanent for qualifying property, much of that can be deducted in year one. Confirm how it applies to your income with your CPA.
No fund, no sponsor and no shared K-1. Just your building, your lease and your tax benefits.
Strong & High Occupancy Rate
The combination of growing demand, limited speculative supply, and the specialized nature of the facilities often results in consistently high occupancy levels, reducing vacancy risk for investors.
Medical office occupancy runs well above most commercial property types, and hospital-adjacent buildings in many markets are effectively full. Vacancy barely moved through the pandemic while conventional office emptied out. Tenants rarely leave space they have spent heavily to build out, so stabilized healthcare properties tend to stay stabilized.
Stable occupancy is exactly what lenders underwrite. A fully leased healthcare property with long remaining lease terms can attract competing offers on rate, leverage and term, but only if multiple lenders actually see it.
We shop your refinance across banks, life companies, CMBS lenders and debt funds, and bring back term sheets side by side.
Supply Constraints and Low Speculative Development
Unlike some other commercial real estate sectors, new healthcare real estate development, particularly MOBs, is typically built only when significant preleasing is secured. This disciplined approach limits oversupply and supports the value of existing properties.
Medical construction costs far more than standard office space once you add imaging suites, medical gas, heavy electrical and procedure rooms. Many states still require certificate-of-need approval for surgical or imaging facilities. As a result, most new projects break ground only with an anchor tenant or health system committed, and the pipeline stays small relative to existing inventory.
That same discipline makes construction financing specialized. Lenders want to see pre-leasing, an experienced team and a realistic budget for tenant improvements.
Building or repositioning a healthcare property? We match construction and bridge requests with lenders who know clinical projects.
High Tenant Stability (“Sticky” Tenants)
Healthcare tenants invest heavily in their space and build patient loyalty around their location, so they rarely move.
A physician practice or surgery center may spend hundreds of dollars per square foot on its build-out, plus years building referral networks tied to that address. Relocating can mean new licensing, new payer contracts and lost patients. That is why medical tenants renew at rates far above conventional office, and why most exercise their renewal options.
For a 1031 exchange, that stability matters. You need replacement property you can hold with confidence, ideally with a long lease, a committed tenant and contractual rent increases.
Exchange into healthcare real estate with tenants built to stay, and own it directly.
Portfolio Diversification Benefits
Healthcare real estate often has a low correlation with the performance of other traditional real estate sectors (like office or retail) and broader economic cycles, making it a valuable tool for investors looking to diversify their portfolios and potentially reduce overall risk.
Healthcare property performance has historically shown low correlation with office, retail and multifamily. Many multifamily owners now face higher insurance, rising expenses and local oversupply, and some are exchanging into management-light healthcare NNN properties to simplify and diversify.
Some exchangers default to Delaware Statutory Trusts, but DSTs typically layer sponsor and broker-dealer fees on top of the property price, and investors give up control. Buying a fee simple healthcare property directly avoids those added fees and keeps decisions in your hands.
Defer capital gains, diversify your holdings and own the asset outright.
Growth Opportunities in Primary & Secondary Markets
Population growth across the Sun Belt and in fast-growing suburbs is driving demand for new outpatient space in markets nationwide.
Texas, Florida, Arizona, the Carolinas and Tennessee continue to add residents faster than the national pace, and health systems are following them with new urgent care, imaging and specialty clinics. Secondary medical hubs anchored by university health systems are seeing tight vacancy and rising rents, while suburbs of gateway metros keep absorbing new outpatient space.
Growth markets move fast, and the strongest buyers show up with financing already lined up.
Buying in a growth market? We line up acquisition financing early so your offer carries real certainty of close.
High Barriers to Entry
Specialized building systems, regulation and financing requirements keep inexperienced developers out of healthcare real estate.
Clinical space requires specialized HVAC and air exchanges, medical gas, lead-lined imaging rooms, reinforced floors for heavy equipment and backup power. Facilities also answer to CMS standards, life-safety codes and state licensing, and some states add certificate-of-need reviews. Those barriers protect existing owners from sudden waves of competing supply.
They also mean not every lender understands the asset. A generalist bank may misprice a surgery center or dialysis clinic that a healthcare-focused lender would compete for.
We know which lenders understand clinical real estate, and we put your deal in front of them.
Growing Institutional and Private Investor Interest
REITs, pension funds and private equity have made healthcare real estate a core holding, and private buyers make up a major share of the market.
Institutional capital has embraced healthcare real estate for its durable income, and healthcare REITs and dedicated funds keep competing for well-leased properties. Yet much of the market is smaller single-asset deals, many under $20 million, where private investors and family offices buy alongside institutions.
You don’t need a fund to participate. You can own the same type of asset institutions target, outright, and choose the tenant, market and lease that fit your goals. Firms that buy properties first and resell them often build their profit into the price. We connect you to available inventory directly.
Institutional-quality healthcare real estate, owned directly, without a reseller’s markup.
How Capital Matching Works
One request, thousands of capital sources and competing term sheets side by side.
Tell us about your property and what you need, whether that’s refinancing a maturing loan, financing an acquisition, construction, bridge capital or a sale-leaseback. We review the deal and match it against lender programs across banks, credit unions, life insurance companies, CMBS conduits, debt funds and bridge lenders.
Then we take it to the lenders whose programs fit, collect term sheets and lay them out side by side so you can compare rate, proceeds, term, recourse and prepayment flexibility. Once you choose, we stay involved through underwriting and closing.
Healthcare real estate is our only focus. Your deal gets matched, not shopped blindly.
Frequently Asked Questions
Is Healthcare Real Estate Fund an investment fund?
No. Healthcare Real Estate Fund is a healthcare real estate capital provider, not a fund. We don’t pool or accept investor money, and we don’t sponsor syndications. For owners and buyers, we arrange financing by matching deals with the right lenders. For investors, we offer direct fee simple ownership only: you buy the healthcare property outright, hold title in your own name or entity, and keep the lease income and depreciation for yourself.
Is Healthcare Real Estate Fund a lender?
No. We don’t lend from our own balance sheet. We match borrowers with our partner banks, credit unions, life insurance companies, CMBS lenders, private and institutional debt funds, and bridge lenders. Each has its own appetite for leverage, term, recourse and property type, so we put your deal in front of the lenders whose programs fit, collect competing term sheets and help you compare them side by side.
What types of healthcare real estate financing do you arrange?
We arrange refinancing for maturing loans, acquisition financing, construction and value-add loans, bridge loans, cash-out refinancing, sale-leasebacks and build-to-suit financing. Our focus is healthcare real estate, from medical office buildings and ambulatory surgery centers to senior care and specialty care facilities. Whether you own your practice’s building, operate multiple locations or are buying a leased investment property, we match the request to lenders who understand clinical real estate.
What healthcare property types do you finance?
Medical office buildings and ambulatory surgery centers, urgent care, dental, dialysis, behavioral health, senior care, and specialty care facilities such as imaging centers, labs, physical therapy and veterinary hospitals. Property type matters to lenders. A generalist bank may misprice a surgery center or dialysis clinic that a healthcare-focused lender would compete for, which is why matching the asset to the right lender drives better terms.
What loan sizes do you work with?
We typically focus on small-balance commercial loans from $2 million to $20 million, along with healthcare real estate portfolios over $50 million. Small-balance healthcare loans are often underserved by large capital markets desks, and portfolio financing calls for lenders with the capacity and healthcare experience to underwrite multiple properties together. If your request falls outside these ranges, tell us about it anyway, and we’ll let you know quickly whether we can help.
When should I start refinancing a maturing loan?
Start planning 12 to 18 months before maturity, and launch the refinance no later than six to eight months out. Early planning gives you time to address issues lenders will ask about, such as upcoming lease expirations or deferred maintenance. Going to market around six months before maturity keeps term sheets current while leaving time to compare rate, proceeds, term and prepayment flexibility across lender types. Waiting until the final few months narrows your options and weakens your negotiating position.
How long does it take to get term sheets?
It depends mostly on how quickly the property documentation comes together: leases or a rent roll, operating statements, tax returns, a recent appraisal or valuation, and borrower financials. Once we have a complete package and make final submissions to lenders, term sheets typically arrive within 1 to 3 weeks. A complete, well-organized package is the single biggest factor in getting fast, competitive responses.
What is a sale-leaseback for a medical practice?
In a sale-leaseback, a practice that owns its building sells the property to an investor and signs a long-term lease to stay in place. The practice turns its real estate equity into cash for expansion, equipment, new locations, a partner buyout or retirement planning, while operations continue without interruption. The investor gets a long-term healthcare tenant. We help practices find buyers and structure terms that fit their plans.
What cap rates do healthcare NNN properties sell at?
Across the healthcare NNN properties we track for sale nationwide, asking cap rates currently run from about 5 to 9 percent, with most between 5.5 and 7 percent and a median near 6.25 percent (as of October 2026). Pricing depends on tenant credit, remaining lease term, rent increases, location and building age. A dialysis clinic leased to a national operator will price differently than a local dental office, so evaluate each deal on its own terms.
Can I take bonus depreciation on a healthcare property?
As a direct fee simple owner, all of the property’s depreciation belongs to you. A cost segregation study can reclassify parts of a medical building, such as specialized electrical, plumbing, cabinetry and site improvements, into shorter-lived categories. With 100% bonus depreciation now permanent for qualifying property acquired after January 19, 2025, much of that reclassified basis can be deducted in year one. How much it offsets depends on your tax situation, so confirm with your CPA.
How is direct ownership different from a DST?
A Delaware Statutory Trust (DST) is a securities offering. You buy a fractional interest alongside other investors, a sponsor controls the property, and sponsor and broker-dealer fees are typically layered into the price. With direct fee simple ownership, you buy the whole property, hold title yourself and make your own decisions about financing, leasing and when to sell, without those added fees. Both can work for a 1031 exchange, but direct ownership keeps control in your hands.